
Epilepsy Medications and Bone Density: What Your DEXA Scan Reveals About How Seizure Drugs Affect Your Bones
Quick answer: Several widely prescribed epilepsy medications, particularly enzyme-inducing drugs such as phenytoin, carbamazepine, and phenobarbital, accelerate bone mineral density loss by disrupting vitamin D metabolism. Sodium valproate also carries a bone-thinning effect through a different mechanism. A bone density DEXA scan is the most reliable way to detect this drug-related bone loss before a fracture occurs, and clinical guidelines recommend it for anyone on long-term antiepileptic therapy with additional risk factors.
If you take medication for epilepsy, you are probably focused on seizure control. That is entirely reasonable. But there is a side effect that rarely makes the conversation between neurologist and patient: gradual, silent bone loss that can progress to osteopenia or osteoporosis over years of treatment.
The UK’s Medicines and Healthcare products Regulatory Agency (MHRA) issued a formal safety update confirming that phenytoin, carbamazepine, primidone, and sodium valproate are associated with decreased bone mineral density, osteopenia, osteoporosis, and an increased risk of fractures in patients taking them long-term. The Epilepsy Society and NICE both recommend vitamin D supplementation and bone health monitoring for people on these drugs.
This article explains the mechanisms behind epilepsy drug-related bone loss, identifies which medications carry the highest risk, and sets out when and why a DEXA scan should be part of your ongoing epilepsy care.
Why Epilepsy Medications Put Your Bones at Risk
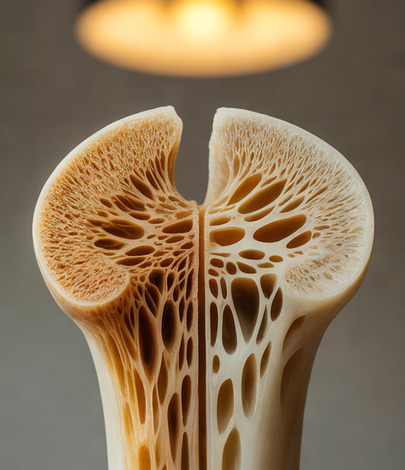
Bone is not a static structure. It is living tissue that constantly remodels itself, with old bone being broken down by osteoclasts and new bone being laid down by osteoblasts. This balance depends on adequate calcium absorption, vitamin D activation, and hormonal signalling.
Several antiepileptic drugs (AEDs) interfere with this process. The best-understood mechanism involves enzyme-inducing AEDs, which include phenytoin, carbamazepine, phenobarbital, and primidone. These drugs activate the cytochrome P450 enzyme system in the liver, which accelerates the breakdown of 25-hydroxyvitamin D into inactive metabolites. The result is a functional vitamin D deficiency even when dietary intake appears adequate.
With less active vitamin D circulating, the body absorbs less calcium from food. To maintain blood calcium levels, parathyroid hormone (PTH) rises, pulling calcium directly from bone. This process, known as secondary hyperparathyroidism, increases bone turnover and gradually reduces bone mineral density.
Sodium valproate is not an enzyme inducer, yet it too is associated with reduced bone density. The exact mechanism remains under investigation, but research published in the journal Metabolism suggests valproate may directly inhibit osteoblast activity and alter bone formation markers independently of vitamin D pathways.
The bone loss is typically gradual, developing over months and years of treatment. Because epilepsy is usually a long-term condition requiring sustained medication, cumulative exposure can be significant.
Which Seizure Drugs Are Most Likely to Cause Bone Loss
Not all epilepsy medications carry the same bone risk. The MHRA’s Drug Safety Update specifically names four drugs with the strongest evidence of bone harm:
- Phenytoin is one of the oldest AEDs and has the most extensive evidence linking it to osteomalacia (softening of bone) and reduced bone mineral density. It is a potent cytochrome P450 inducer.
- Carbamazepine is another enzyme-inducing drug with well-documented effects on vitamin D metabolism. Studies published in Calcified Tissue International show measurable bone density reductions in patients on long-term carbamazepine therapy.
- Phenobarbital and primidone are strong enzyme inducers that significantly increase vitamin D clearance. Primidone is partially metabolised to phenobarbital, so the bone effects compound.
- Sodium valproate is associated with decreased bone mineral density through mechanisms that appear to be independent of vitamin D metabolism.
Topiramate has also been flagged as a potential concern for bone health, though the Epilepsy Society notes that more research is needed to confirm this link.
In contrast, newer AEDs such as lamotrigine, levetiracetam, and lacosamide may carry a lower bone risk. A study in Arquivos de Neuro-Psiquiatria comparing bone mineral density in patients on levetiracetam versus older AEDs found no significant bone density reduction with levetiracetam monotherapy. However, the evidence is not yet conclusive enough to declare these drugs entirely bone-safe, particularly in polytherapy regimens where they are combined with enzyme-inducing drugs.
How a DEXA Scan Detects Drug-Related Bone Loss Early
Drug-related bone loss does not cause symptoms until a fracture occurs. You cannot feel your bone density declining. This is precisely why a bone density DEXA scan is so valuable for people on long-term epilepsy medication.
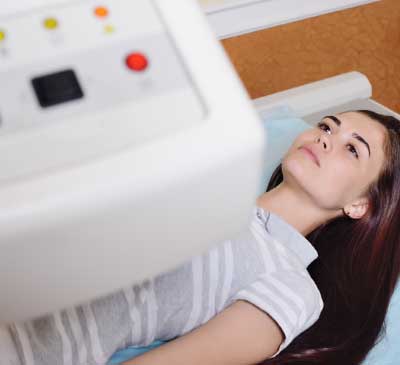
A dual-energy X-ray absorptiometry (DEXA) scan measures bone mineral density at the lumbar spine and hip, the two sites most vulnerable to osteoporotic fracture. The scan takes approximately ten minutes, uses a very low dose of radiation, and produces a T-score that compares your bone density to that of a healthy young adult.
A T-score between -1.0 and -2.5 indicates osteopenia, meaning your bone density is lower than expected but not yet in the osteoporosis range. A T-score of -2.5 or below indicates osteoporosis. For someone taking an enzyme-inducing AED, catching a T-score drift from normal into osteopenia is the ideal moment to intervene, well before fracture risk becomes clinically significant.
Because AED-related bone loss is gradual, serial DEXA scans performed every one to two years can track the trajectory of your bone density over time. This allows your clinician to see whether supplementation, lifestyle changes, or a medication review is slowing or reversing the decline. To learn more about how this technology works, see our guide to how DEXA scanning works.
Who Should Get a DEXA Scan If They Take Epilepsy Medication
The MHRA identifies several groups at particular risk of AED-related bone loss. If any of the following apply to you, a baseline DEXA scan is worth discussing with your doctor:
- You have been taking phenytoin, carbamazepine, phenobarbital, primidone, or sodium valproate for two years or more.
- You have limited sun exposure due to your lifestyle, work patterns, or seizure-related restrictions on outdoor activity.
- You have a low dietary calcium intake or follow a restricted diet.
- You are immobilised or have reduced mobility, whether from seizure-related injuries or other conditions.
- You are a postmenopausal woman, as the combination of oestrogen decline and AED use compounds bone loss.
- You have a family history of osteoporosis, particularly a parental hip fracture.
- You take corticosteroids alongside your epilepsy medication.
- You smoke or drink alcohol regularly.
Men on long-term AEDs should not assume they are exempt. Research published in Neurology has shown that male patients on enzyme-inducing AEDs also experience measurable reductions in bone mineral density, particularly at the hip.
If you are unsure whether your specific medication poses a bone risk, your neurologist or GP can advise. But a DEXA scan provides objective data that removes the guesswork.
Protecting Your Bones While Staying on Your Epilepsy Treatment
The most important point is this: you should never stop or change your epilepsy medication without medical advice. Uncontrolled seizures carry risks that far outweigh the bone effects of most AEDs. The goal is to protect your bones while maintaining effective seizure control.
Vitamin D supplementation is the first line of defence. NICE recommends that people taking epilepsy medicines linked to bone problems should take vitamin D supplements. The Epilepsy Society advises that everyone in the UK should supplement vitamin D during autumn and winter, and those on bone-affecting AEDs may benefit from year-round supplementation. Your GP can check your 25-hydroxyvitamin D level with a blood test and adjust the dose accordingly.
Calcium intake matters alongside vitamin D. The Epilepsy Society notes that calcium supplementation is advisable if your dietary intake falls below 700 mg per day, rising to 1,000 mg if osteoporosis has been diagnosed. Good dietary sources include dairy products, fortified plant milks, leafy green vegetables, and tinned fish with edible bones.
Weight-bearing exercise stimulates bone formation directly. Walking, dancing, stair climbing, and resistance training all apply mechanical load to bone, triggering osteoblast activity. Even moderate activity three to four times per week can slow bone density decline.
Lifestyle factors also play a role. Stopping smoking, reducing alcohol intake, and maintaining a healthy body weight all support bone health. If you have been through menopause, discussing hormone replacement therapy with your clinician may offer additional bone protection.
Newer Epilepsy Drugs and Bone Safety
If you are concerned about bone health, you may wonder whether switching to a newer antiepileptic drug could reduce your risk. The evidence is encouraging but not yet definitive.
Lamotrigine, levetiracetam, and lacosamide do not induce cytochrome P450 enzymes and therefore do not accelerate vitamin D breakdown in the same way as phenytoin or carbamazepine. Observational studies and small clinical trials suggest that patients on these newer agents tend to have better bone mineral density than those on older enzyme-inducing drugs.
A Danish study published in Calcified Tissue International found that adult patients treated with newer AEDs had bone mineral density values closer to population norms compared with those on phenytoin or carbamazepine. However, the researchers cautioned that follow-up periods were relatively short and that long-term bone safety data for newer drugs remains limited.
Switching medication is not always straightforward. Seizure control must come first, and not every patient responds equally to every drug. Any medication change should be led by your neurologist, ideally supported by DEXA scan data showing your current bone status so the decision is informed rather than speculative.
We covered the broader picture of how prescription drugs affect bone health in our guide to medications that cause bone loss, which includes additional drug classes worth reviewing if you take multiple prescriptions.
Frequently Asked Questions
Can epilepsy medication cause osteoporosis?
Yes. The MHRA has confirmed that long-term use of phenytoin, carbamazepine, primidone, and sodium valproate is associated with decreased bone mineral density, osteopenia, osteoporosis, and an increased risk of fractures. The risk increases with duration of treatment and the presence of additional risk factors such as low vitamin D, limited physical activity, or postmenopausal status.
How often should I get a DEXA scan if I take epilepsy medication?
If your baseline DEXA scan is normal and you have no additional risk factors, rescanning every two years is a reasonable interval. If your scan shows osteopenia or if you are on a high-risk medication such as phenytoin, your clinician may recommend annual monitoring to track the rate of change.
Does levetiracetam cause bone loss?
Current evidence suggests that levetiracetam is less likely to cause bone loss than older enzyme-inducing drugs. It does not induce cytochrome P450 enzymes and therefore does not accelerate vitamin D metabolism. However, long-term studies are still limited, and bone health monitoring remains advisable for anyone on prolonged AED therapy.
Should I stop my epilepsy medication if my DEXA scan shows bone loss?
No. You should never stop or change epilepsy medication without medical advice. Uncontrolled seizures carry serious risks. If your DEXA scan reveals bone loss, the first steps are typically vitamin D and calcium supplementation, lifestyle modifications, and a discussion with your neurologist about whether a medication review is appropriate.
Does vitamin D supplementation reverse bone loss from epilepsy drugs?
Vitamin D supplementation helps restore calcium absorption and can slow the rate of bone density decline. Whether it fully reverses established bone loss depends on the degree of damage and the duration of deficiency. It is most effective when combined with adequate calcium intake and weight-bearing exercise. Your GP can monitor your vitamin D levels and adjust your dose as needed.
What This Means for You
If you take medication for epilepsy, particularly phenytoin, carbamazepine, phenobarbital, primidone, or sodium valproate, your bones may be losing density without any warning signs. The clinical evidence is clear: these drugs alter the biochemical pathways that maintain bone strength, and the effect compounds over years of treatment.
A body composition DEXA scan gives you a precise, objective measurement of your bone mineral density at the sites that matter most. It takes ten minutes, involves minimal radiation, and provides the data you and your clinician need to make informed decisions about supplementation, lifestyle changes, or medication review.
At DEXA London, we see patients who have been on epilepsy medication for years without ever having their bone density checked. By the time symptoms appear, significant bone loss has already occurred. A DEXA scan catches the problem early, when intervention is most effective.
To book your DEXA scan at our Harley Street clinic, call 0207 637 8227 or visit dexa.london. Our clinical team can guide you through the process and help you understand what your results mean for your ongoing epilepsy care.