
Denosumab (Prolia) and Bone Density: What Your DEXA Scan Reveals About Whether Your Osteoporosis Treatment Is Working
If you have been prescribed denosumab, sold under the brand name Prolia, you are taking one of the most effective medications available for osteoporosis. Denosumab is a six-monthly injection that slows bone breakdown at a cellular level, and the evidence behind it is some of the strongest in osteoporosis medicine. A landmark trial following patients for ten years found that denosumab increased bone mineral density at the lumbar spine by over 21 per cent and at the total hip by more than 9 per cent, with fracture rates remaining consistently low throughout that period.
Yet many patients on denosumab have questions that a prescription alone does not answer. How will I know it is working? How long do I need to stay on it? What happens if I miss a dose or want to stop? These are not hypothetical worries. The answers sit in your DEXA scan results, and understanding them can make the difference between passive treatment and informed, confident management of your bone health.
Quick answer: Denosumab works by blocking RANKL, a protein that activates the cells responsible for breaking down bone. DEXA scans are the primary tool for monitoring whether the treatment is improving your bone density. Crucially, denosumab must never be stopped without a planned transition to another medication, because bone density can drop rapidly after discontinuation, sometimes below pre-treatment levels, with a significant increase in vertebral fracture risk.
How Denosumab Works Inside Your Bones
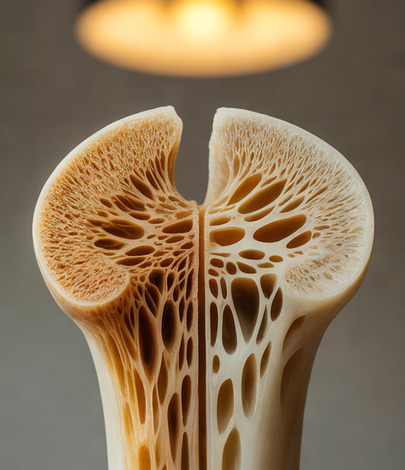
Bone is not a static structure. It is a living tissue in constant renewal, with specialised cells called osteoclasts breaking down old bone and osteoblasts building new bone to replace it. In healthy adults, this cycle of resorption and formation stays roughly in balance. In osteoporosis, resorption outpaces formation, and the internal scaffold of bone, the trabecular lattice, thins and weakens.
Denosumab is a monoclonal antibody that targets a protein called RANKL (Receptor Activator of Nuclear factor Kappa-B Ligand). RANKL is the signal that tells osteoclast precursors to mature into active bone-resorbing cells. By binding to RANKL and blocking that signal, denosumab reduces the number and activity of osteoclasts. With fewer cells breaking bone down, the balance tips back towards formation, and bone mineral density rises.
Unlike bisphosphonates, which embed into bone mineral and continue working for months or years after the last dose, denosumab is a circulating antibody with a half-life of roughly 26 days. It does its job while it is in the bloodstream and stops working once it clears. This is what makes denosumab so effective while you take it, and so important to manage carefully if treatment is ever paused or stopped.
What the Clinical Evidence Shows
The strongest evidence for denosumab comes from the FREEDOM trial and its long-term extension, which followed postmenopausal women with osteoporosis for up to ten years. The results were striking. Women who received denosumab for the full ten years gained an average of 21.7 per cent in lumbar spine bone density and 9.2 per cent at the total hip, measured from baseline. Those who crossed over from placebo after three years still achieved gains of 16.5 per cent at the spine and 7.4 per cent at the hip over the following seven years.
Fracture rates remained low throughout the study period. The annual incidence of new vertebral fractures stayed between 0.9 and 1.86 per cent, and nonvertebral fractures between 0.84 and 2.55 per cent. These rates were lower than would be expected in an untreated population of the same age and fracture risk.
In the United Kingdom, the National Institute for Health and Care Excellence (NICE) recommends denosumab as a treatment option for postmenopausal women whose bone density and fracture risk meet specific thresholds, particularly when bisphosphonates are unsuitable or not tolerated. The National Osteoporosis Guideline Group (NOGG) 2024 guidelines similarly position denosumab as a first-line treatment for high-risk patients.
How a DEXA Scan Monitors Your Response to Denosumab
A DEXA scan is the gold standard for tracking whether denosumab is doing its job. It measures bone mineral density at the lumbar spine and hip, the two sites most vulnerable to osteoporotic fracture, and expresses the result as a T-score (how your density compares with a healthy young adult) and a Z-score (how it compares with others your age).
Most clinicians recommend a baseline DEXA scan before starting denosumab, then a follow-up at 12 to 24 months. What you should see is a measurable increase in bone mineral density at one or both sites. The expected gain in the first year is typically around 3 to 6 per cent at the lumbar spine and 1 to 3 per cent at the total hip, with further gains accumulating in subsequent years.
If your DEXA scan shows stable or increasing density, the treatment is working. If density drops by more than the measurement error of the scanner (known as the least significant change, usually around 3 to 5 per cent depending on the site), that may signal a problem: missed doses, poor calcium or vitamin D intake, or an underlying condition accelerating bone loss.
Some specialists also use blood tests for bone turnover markers, such as CTX (a marker of bone resorption) and P1NP (a marker of bone formation), alongside DEXA. A suppressed CTX level confirms that denosumab is actively reducing bone breakdown. However, DEXA remains the definitive measure of whether bone density is improving.
Why You Must Never Stop Denosumab Without a Plan
This is the single most important thing any patient on denosumab needs to understand. Unlike bisphosphonates, which leave a residual protective effect in bone for years after the last tablet or infusion, denosumab clears from the body within months. When it does, the osteoclasts that were held in check come roaring back, and bone resorption can accelerate to levels above what they were before treatment started.
This phenomenon, called rebound bone loss, is well documented. In the first 12 months after stopping denosumab without transitioning to another therapy, patients can lose 5 to 11 per cent of their bone density, and the loss can continue for up to 30 months at the hip. Published cohort data show a three- to five-fold increase in the risk of vertebral fractures after discontinuation, with the greatest risk occurring 6 to 18 months after the last injection. Multiple vertebral fractures in quick succession are the most feared complication, occurring in an estimated 8 to 10 per cent of patients who stop without a follow-on treatment.
Even delaying a scheduled injection by as little as four months has been associated with increased fracture risk in registry studies. The message is clear: do not skip, delay, or stop denosumab injections without discussing a transition plan with your prescribing doctor.
Transitioning Off Denosumab Safely
When a decision is made to stop denosumab, whether because bone density has improved sufficiently, because of side effects, or for any other reason, the recommended approach is to transition to a bisphosphonate. The goal is to lock the bone density gains into the mineral matrix before the rebound effect takes hold.
Current expert guidance, including the 2024 NOGG recommendations, suggests starting zoledronic acid (an annual intravenous bisphosphonate) or oral alendronate approximately six months after the last denosumab injection. The bisphosphonate is typically continued for one to two years, with DEXA monitoring at the point of transition and again at 12 months to confirm that density is being maintained.
Blood markers of bone turnover can guide the timing. If CTX begins to rise above the target threshold (typically 280 nanograms per litre) at three or six months post-transition, it may indicate that the bisphosphonate is not fully suppressing the rebound, and a second dose of zoledronic acid or a switch in strategy may be needed.
Teriparatide (a bone-building parathyroid hormone analogue) is generally not recommended as a follow-on after denosumab, because the evidence for preventing rebound bone loss with teriparatide is limited. If you are considering stopping denosumab, your specialist should map out the transition well in advance.
Common Questions Patients Ask About Denosumab and DEXA
How long should I wait after my Prolia injection before having a DEXA scan?
There is no strict requirement to wait. However, most clinicians schedule the DEXA at least two to three months after the injection, so the scan captures the treatment effect rather than an acute response. A scan at 12 months from the start of treatment is standard.
Can denosumab actually cure osteoporosis?
Denosumab does not cure osteoporosis, but it can improve bone density to the point where your T-score moves out of the osteoporotic range (below -2.5) and into the osteopenic or even normal range. However, the underlying tendency towards bone loss persists, which is why stopping without a transition plan causes problems.
What if my DEXA results are not improving after a year on Prolia?
First, confirm that injections have been given on schedule every six months. Then check vitamin D levels (ideally above 75 nanomoles per litre in the UK) and daily calcium intake (at least 700 to 1,000 milligrams from diet and supplements combined). If all of these are in order and density is still falling, your doctor may investigate secondary causes of bone loss, such as hyperparathyroidism, coeliac disease, or other conditions that accelerate resorption.
Is it safe to stay on denosumab for many years?
The FREEDOM extension study followed patients for ten years with continued bone density gains and no new safety signals beyond those seen in the first three years. Rare side effects such as osteonecrosis of the jaw and atypical femoral fractures have been reported but remain uncommon. For most patients, the benefit of continued treatment outweighs the risk, particularly when the alternative is stopping without a plan.
I missed my six-monthly injection. What should I do?
Contact your prescribing clinic as soon as possible to reschedule. Even a short delay increases the window in which rebound bone loss can begin. A DEXA scan and bone turnover markers may be advisable if the gap exceeds two to three months beyond the scheduled date.
Frequently Asked Questions
What is denosumab (Prolia) used for?
Denosumab is prescribed for the treatment of osteoporosis in postmenopausal women and in men at increased risk of fracture. It is also used for bone loss caused by hormone-deprivation therapy in patients with breast or prostate cancer.
How does denosumab differ from bisphosphonates?
Both reduce bone resorption, but they work differently. Bisphosphonates (such as alendronate and zoledronic acid) bind directly to bone mineral and remain active for years after the last dose. Denosumab is a circulating antibody that works only while it is in the bloodstream, which means its effect stops when the drug clears. This makes the transition off denosumab more clinically important.
How often do I need a DEXA scan while on Prolia?
A baseline scan before treatment and a follow-up at 12 to 24 months is standard. Your specialist may recommend more frequent scanning if there are concerns about treatment response or if you are transitioning off denosumab. At DEXA London, we provide clinical-grade bone density scans with same-day results at our Harley Street clinic.
Can I have a DEXA scan while receiving denosumab?
Yes. Denosumab does not interfere with the accuracy of a DEXA scan. You can have a scan at any point during your treatment cycle.
What happens if denosumab does not improve my bone density?
If bone density is not improving despite regular injections, your doctor will investigate other factors: vitamin D deficiency, inadequate calcium intake, undiagnosed conditions affecting bone metabolism, or medication interactions. A lack of response does not necessarily mean the drug has failed; it often points to a correctable issue.
What This Means for You
Denosumab is a powerful tool for rebuilding bone density, and your DEXA scan is the way you and your doctor measure whether that tool is working. The evidence from large clinical trials shows substantial, sustained gains in bone mineral density at the spine and hip over years of treatment, with fracture rates that remain low.
The critical point to take away is that denosumab is not a medication you simply stop when you feel better. It requires ongoing monitoring and, if discontinuation is appropriate, a carefully planned transition to a bisphosphonate to protect the density gains you have built up. Rebound bone loss after stopping denosumab is real, well documented, and preventable with proper planning.
If you are on denosumab and have not had a DEXA scan in the past 12 to 24 months, or if you are considering stopping treatment, a bone density assessment is an important next step. We covered the role of bisphosphonates in managing bone density in our guide to bisphosphonates and bone density on a DEXA scan, which may be a useful companion read if your doctor is discussing a switch in medication.
At DEXA London, we provide clinical-grade bone density and body composition scans at our Harley Street clinic, with results explained on the day by a qualified clinician. To book a bone density DEXA scan, visit our website or call us on 0207 637 8227.